Children's health
Authors
Beth Duff-Brown
News Type
News
Date
Paragraphs

In the slums of Nairobi, where sexual assault is as commonplace as it is taboo to discuss, a team of Kenyan counselors is teaching kids that no means no.

The girls learn to shout — “Hands off my body!” — and throw an elbow jab or good kick to the groin. The boys are encouraged to stand up for the girls and fight against the social traditions that have normalized rape.

Perhaps most effectively, the children learn how to talk themselves out of precarious situations, use clever diversions and speak loudly when faced with potential attackers, through a series of role-playing exercises that promote healthy gender norms.

The behavioral intervention appears to be working. Observational studies have inferred that the incidence of rape has dropped dramatically — perhaps even by half.

But how do those who are devoted to protecting these girls from sexual violence prove to themselves and their donors that their efforts and dollars are making a difference?

This is where Mike Baiocchi comes in. The Stanford statistician and his team of researchers and students are conducting the largest-ever randomized trial of its kind in an effort to place rare, high-quality quantitative proof alongside the more common observational evidence.

“That’s what I specialize in: messy, real-world data where you try and prove the cause-and-effect relationship,” said Baiocchi, PhD, an assistant professor of medicine at the Stanford Prevention Research Center in the School of Medicine.

Rosenkranz Prize 2017 winner Mike Baiocchi and his partner, Clea Sarnquist, both of Stanford Medicine, conduct research on the ground in Nairobi, Kenya, to determine whether a rape prevention program is truly making a difference. Rosenkranz Prize 2017 winner Mike Baiocchi and his partner, Clea Sarnquist, both of Stanford Medicine, conduct research on the ground in Nairobi, Kenya, to determine whether a rape prevention program is truly making a difference.

Rosenkranz Prize 2017 winner Mike Baiocchi and his partner, Clea Sarnquist, both of Stanford Medicine, conduct research on the ground in Nairobi, Kenya, to determine whether a rape prevention program is truly making a difference.


Baiocchi and his team have designed a closed-cohort study that will track the behavior of about 5,000 girls and 1,000 boys enrolled in the No Means No Worldwide project, which is training 300,000 girls and boys in Kenya and Malawi to prevent rape and teen pregnancy.

This innovative approach to applying math to a real-world problem won him this year’s Rosenkranz Prize for Health Care Research in Developing Countries.

“The entire Rosenkranz selection committee was highly impressed both with the rigor of Mike’s work — which he publishes in top journals in the field of statistics — as well as his unconventional and potentially very impactful work on the prevention of gender-based violence in illegal settlements around Nairobi,” said Grant Miller, PhD, an associate professor of medicine and core faculty member at Stanford Health Policy.

Miller chairs the committee that selects the winners of Stanford Health Policy’s annual $100,000 prize, which goes to promising young Stanford researchers who are investigating ways to improve health care and health policy in developing countries.

Overwhelming Prevalence of Sexual Violence

In the United States, according to the Centers for Disease Control and Prevention, nearly one in five women are raped. The World Health Organization estimates that globally, one in three women experience sexual or physical violence.

In Kenya, national surveys reveal that as many as 46 percent of Kenyan women experience sexual assault as children.

“In the roughest part of the Nairobi slums, 20 to 25 percent of high school girls will be raped this year,” said Baiocchi. “This program, however, looks like it is having the ability to cut that in about half. Our job is to tease out the evidence through careful measurement and design of experiment.”

To do this, Baiocchi and other members of the Stanford Gender-Based Violence Collaborative have traveled to Nairobi to collect baseline data. His partner is Clea Sarnquist, DrPH, a senior research scholar for the Global Child Health Program in the Stanford Department of Pediatrics.

Several pilot evaluations of the program, published in 2014 in Pediatrics, found that more than half of 2,000 high school girls who had completed the self-defense course had used their newfound skills to fend off sexual harassment or rape.

But Lee Paiva, the San Francisco-based founder of No Means No Worldwide, wanted proof. She told Stanford Medicine magazine last year that since establishing training in 2010, she often wondered about the true effectiveness of the program.

“A little voice inside me said, `What did you teach them?’” she said. “What did those kids actually get? What is that money really going to do?”

She determined that she wasn’t going to move forward on the program until she could answer those questions. That is when she turned to Stanford.

Expanding on their initial work, Baiocchi and Sarnquist spent several months last year, working with their Kenyan partners, Ujamaa-Africa and the African Institute for Health and Development, in 90 schools in the poorest parts of Nairobi to establish the largest randomized trial of its kind.

They interviewed the girls who have taken part in the six-week empowerment and self-defense program taught by Kenyans who grew up in the same neighborhoods and are familiar with the local culture.

“It’s hard not to be extraordinarily excited when you watch these girls; they’re play-acting and just being kids, but you are also watching them evolving and creating new ways to deal with these situations,” said Baiocchi.The team is now tracking a fixed group of  5,000 girls and 1,000 boys, ages 10 to 16, over two years. This will give the researchers a better understanding of just how the girls are adopting the training and readapting to societal demands.
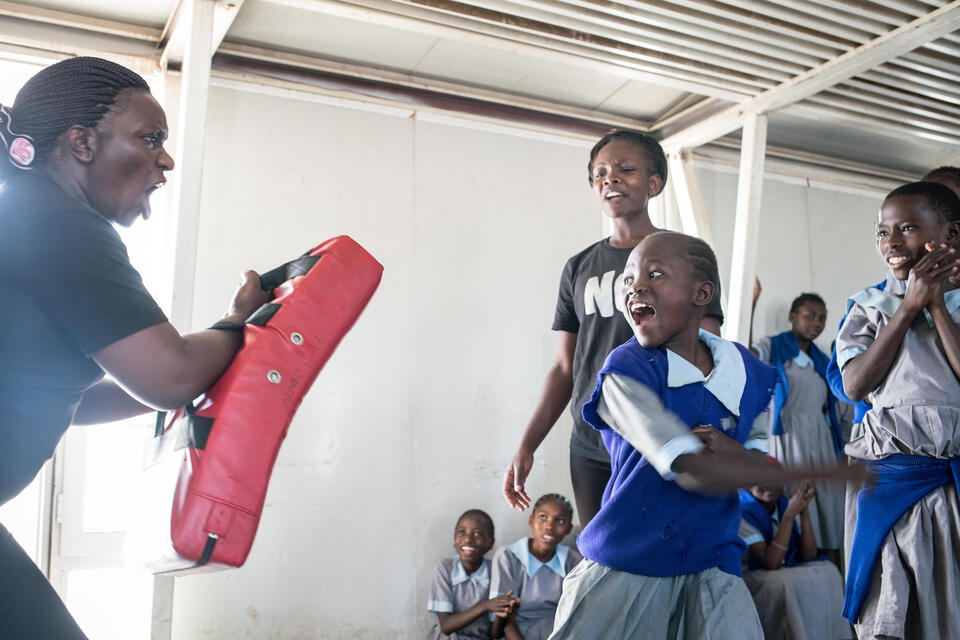
Image


“Doing a randomized trial is slow, expensive, and — if I’m being totally honest — anxiety-inducing because everything is laid so bare and you put things in motion today that won’t be resolved for another two years,” Baiocchi said. “But the reward is extraordinarily high-quality data that helps you understand what’s really going on. We need this level of evidence if we’re going to take on such a difficult problem.”

Since using math to measure the benefits of gender-based violence prevention interventions is a relatively new science, Baiocchi said the team is adopting the highest level of rigor, equivalent to what it would take to get their results through the FDA.

The randomized controlled trial is being funded by the UK Department of International Development as part of its What Works to Prevent Violence initiative, with the goal of determining whether the behavioral intervention is effective in preventing sexual assault.

A Need to Do Good

Baiocchi notes both his parents are nurses, his brother is a nurse who is married to a nurse. Public health and service runs through the family DNA.

“So, when I came out as being a math person, I knew that I also had to do good.”

Since receiving his PhD in statistics from The Wharton School at the University of Pennsylvania in 2011, Baiocchi has worked on ways to improve high-risk infant deliveries, school-based earthquake risk reduction in Nepal, bail reform in the United States, improving cardiothoracic surgical care, as well as cancer and cardiovascular disease prevention in China.

The Kenya project team, which includes eight Stanford undergraduate and graduate students, intends to share their results, putting out open-source tutorials that will explain their statistical methods and provide sample code and data.

Image

“We want to make it really easy for people in this area to start having a similar language so we can better communicate and build on this science,” he said.

The Rosenkranz funding will help to build this open-source site and support the Stanford team in their research and travel to Kenya and other countries.

The award’s namesake, George Rosenkranz, who holds a doctorate in chemistry, first synthesized cortisone in 1951, and later progestin, the active ingredient in oral birth control pills. He went on to establish the Mexican National Institute for Genomic Medicine, and his family created the Rosenkranz Prize in 2009.The award embodies Rosenkranz’s belief that young scientists hold the curiosity and drive necessary to find alternative solutions to longstanding health-care dilemmas.

Baiocchi called Rosenkranz’s work to help women take control of their reproductive health “revolutionary,” and is humbled to now be on the list of the other prizewinners, Eran Bendavid, Sanjay Basu, Marcella Alsan, Jason Andrews and Ami Bhatt.

“Our work is a continuation of the powerful changes Dr. Rosenkranz set in motion,” he said.

And what really matters, Baiocchi said, are the end results.

“There are a number of girls who are not going to get raped this year because of what we are doing,” he said. “And we know that if someone doesn’t get assaulted, that leads them to having a better life — it’s an extraordinarily virtuous cycle.”

[[{"fid":"226830","view_mode":"crop_870xauto","fields":{"format":"crop_870xauto","field_file_image_description[und][0][value]":"","field_file_image_alt_text[und][0][value]":false,"field_file_image_title_text[und][0][value]":false,"field_credit[und][0][value]":"","field_caption[und][0][value]":"","thumbnails":"crop_870xauto","alt":"","title":""},"type":"media","field_deltas":{"6":{"format":"crop_870xauto","field_file_image_description[und][0][value]":"","field_file_image_alt_text[und][0][value]":false,"field_file_image_title_text[und][0][value]":false,"field_credit[und][0][value]":"","field_caption[und][0][value]":"","thumbnails":"crop_870xauto","alt":"","title":""}},"link_text":null,"attributes":{"class":"media-element file-crop-870xauto","data-delta":"6"}}]]

Hero Image
kenya rosenkranz3
Nichole Sobecki
All News button
1
Paragraphs

Most civilian casualties in war are not the result of direct exposure to bombs and bullets; they are due to the destruction of the essentials of daily living, including food, water, shelter, and health care. These “indirect” effects are too often invisible and not adequately assessed nor addressed by just war principles or global humanitarian response. This essay suggests that while the neglect of indirect effects has been longstanding, recent technical advances make such neglect increasingly unacceptable: 1) our ability to measure indirect effects has improved dramatically and 2) our ability to prevent or mitigate the indirect human toll of war has made unprecedented progress. Together, these advances underscore the importance of addressing more fully the challenge of indirect effects both in the application of just war principles as well as their tragic human cost in areas of conflict around the world.

All Publications button
1
Publication Type
Journal Articles
Publication Date
Journal Publisher
Daedalus
Authors
Paul H. Wise
-

May 25th Schedule for Child Health and Immigration Conference

Children in Immigrant Families and National Immigration Policy


8:30- 8:40        Welcome Drs. Mendoza, Sanders, and Wang

8:40-9:20       Demographics of Children in Immigrant Families

                          Jeffrey Passel, Ph.D., Senior Demographer, Hispanic Pew Research Center

9:20 -10:00    National Immigration Policy and Its Implications for Children in Immigrant Families

Bill Hing, JD, Professor of Law and Director of the Immigration and Deportation Defense Clinic, University of San Francisco, School of Law

Break 10 minutes

10:10- 11:10  Policy Research on CIF: Improving Health and Well Being (Duncan Lawrence, Ph.D.)

  Fernando Mendoza, MD, MPH – Professor of Pediatrics, Stanford University

                          Stanford Immigration Policy Lab

                                    Jens Hainmueller, Ph.D., Professor of Political Science

                                    David Laitin, Ph.D., Professor of Political Science

                                    Tomas Jimenez, Ph.D. – Associate Professor of Sociology

                          Florencia Torche, Ph.D. –Professor of Sociology, Stanford University

11:10 -12:10 Federal, State, and Regional Actions on Immigration Policy (Sherri Sager)

                          Zoe Lofgren, JD –(by video) Congresswoman 19th Congressional District, California

  Elizabeth Baca, MD, MPA, Sr. Health Advisor California Governor's Office of Planning and Research

  Jonathan Blazer, JD – Special Assistant Attorney General, California Dept. of Justice

  David Cortese, JD –President, Santa Clara County Board of Supervisors

12:10 -1:00 Lunch


Regional and Local Concerns for Children in Immigrant Families


1:00-2:20       Immigration and the Health and Educational Systems (David Alexander, MD)

                          Chris Dawes, MBA – CEO, Lucile Packard Children’s Hospital

                          Stephen Harris, MD – Santa Clara Valley Medical Center, Chair Dept. of Pediatrics

                          Reymundo Espinoza, MPH – Executive Director Gardner Family Health Network

                          Sara Cody, MD -Director, Public Health Department, Santa Clara County

                          Juan Cruz, MA– Superintendent, Franklin-McKinley School District

Break 10 minutes


2:30 -3:40       Health and Mental Health of Children in Immigrant Families (Yvonne Maldonado, MD)

                          Elena Fuentes Afflick , MD, MPH – Professor of Pediatrics, UCSF

                          Glenn Flores, MD – Chair, Health Policy Research, Medica Research Institute, .

                          Ryan Matlow, Ph.D. – Director of Community Research for Early Life Stress, Stanford

Break 10 minutes


3:50-4:50       Advocating for Children in Immigrant Families (Lee Sanders, MD)

                          Lisa Chamberlain, MD, MPH – Associate Professor of Pediatrics, Stanford; Director, Pediatric Advocacy Program

                          Maricela Gutierrez –Exe. Dir. Services, Immigration Rights, and Education Network

                          Dana Weintraub, MD - Assistant Professor; Medical Director, Peninsula Family Advocacy Program

                          Stacey Hawver, JD – Legal Director, Peninsula Family Advocacy Program


4:50 to 5:00    Closing Remarks –Fernando Mendoza, MD, MPH, -Professor of Pediatrics


5:00-6:00       Reception

Conferences
Authors
News Type
News
Date
Paragraphs

Like any energetic 7-year-old, your daughter loves running around outside, playing with her friends and kicking around a soccer ball. So you’re concerned when she starts losing energy. She looks pale and refuses to eat. You take her to the pediatrician, and her test results show the worst: she has leukemia. Once you work through the shock, you do you what any parent would do: find the best possible care to get her through it. But where do you go?

Health care for children is different from care for adults. Treating kids requires doctors who are experienced with their unique needs, and according to Stanford pediatricians Paul Wise and Lisa Chamberlain, this experience is developed and lives in children’s hospitals.

And these facilities are highly dependent on Medicaid.

“Children are the poorest segment of the United States population,” said Wise, a Stanford Health Policy core faculty member.

Nearly one out of every five children lives below the poverty line, according to the United States Census Bureau. Very few children need extensive health care, but of those that do, about 44 percent rely on Medicaid or other public insurance programs.

Because so many of their patients use Medicaid, these children’s hospitals need reimbursements from the program to support their services. Without this income, some might have to downsize or even shut down, and if they do, services would suffer for all children.

“If you want to kill rich kids, cut Medicaid,” said Wise. “If you’re a rich kid with a serious chronic problem, you’re going to want facilities that provide high-quality care. Those facilities are intensely dependent on Medicaid.”

If the American Health Care Act (the Republican replacement for Obamacare) passes Congress, Medicaid will convert to a per capita cap system. Instead of providing coverage to all who meet its criteria — which is primarily based on income and need — the federal government would cap how much money the federal government could provide each person.

Wise and Chamberlain worry that a set amount allocated for states or individuals would not be able to keep up with health industry inflation, causing payments to effectively decrease over time. They are also concerned that children would be particularly affected by these changes because their medical needs are so different from adults’.

“Caring for seriously ill children requires a wide range of services and specialists, from pediatric surgeons to speech therapists to hospital teachers who make sure kids don’t fall behind,” said Chamberlain. “In pediatrics we work as a team — and cutting Medicaid will reduce our ability to do that.”

Not only would the funds available for child health coverage erode, but according to Wise, the focus on adult health concerns in the emerging Medicaid changes could, without immediate attention, undermine 40 years of progress in developing strong, regionalized child health systems.

Providing for children’s needs should be simple because their expenditures are relatively low. Child health care makes up less than nine percent of all federal health expenditures in the United States.

But because the health policy debate in the United States focuses on older populations, children are often left out.

“I think it’s really important that we have these conversations about the unique needs of children,” said Chamberlain.

Wise and Chamberlain hope to alert policy-makers to the fiscal needs of children and how they affect care for all kids.

“Our elected officials have to cope with a wide range of issues, and they welcome engaged professionals exchanging ideas about active legislation,” said Chamberlain. “Those conversations really matter – now is the time to let them hear what we think.”

To hear more from Wise and Chamberlain about child health and Medicaid, listen to their podcast on World Class:

Hero Image
gettyimages 107429730
Getty Images
All News button
1
Authors
Lisa Chamberlain
News Type
Commentary
Date
Paragraphs

I remember two things about my patient, Maria, a tiny baby who was born a little early. One was her large, beautiful eyes. The other was that when I put my stethoscope on her chest, I heard an enormous heart murmur. Maria had been born with a serious heart condition that would change her life and the life of her mom.

Good patient care at a time like this involves much more than treating a child’s heart. At that first appointment, Maria (not her real name), her mother and I began a long journey punctuated by multiple hospitalizations, surgeries and procedures.

Maria was born at Lucile Packard Children’s Hospital Stanford and lived with her mom in East Palo Alto. As her general pediatrician at Ravenswood Family Health Center, I came to know them both well. I focused on helping the tiny infant gain weight, so that she would be strong enough to undergo her heart surgeries. We brought in the Women, Infants and Children program to support her nutrition. I explained to her mom what the surgeries would do. I reviewed what Maria’s medicines were for, and when her mother couldn’t pay for them I helped gain authorization from county staff, who were able to get them dispensed at the pharmacy. When I realized Maria’s mom didn’t have enough money for food (due to many absences at work), I made sure she applied for food stamps.

Image
l chamberlain 6752

My experience with Maria coincided with my research at Stanford involving access to care for kids in California. As a result of the research, I spent part of my time in Sacramento, working with legislators on changes to the California Children’s Services program. This program is critical to the care of low-income children with serious medical conditions. My research, which involved analyzing data on publicly insured pediatric care like Maria’s, showed that access to high-quality care for low-income kids was pretty good in California compared with other states, but that there was variation among its 58 counties.

While working on the program’s reform in Sacramento, I spent time in countless staff meetings, public hearings and hallway discussions. I often thought about Maria, whose life depended on CCS. The research data I brought to these negotiations were as important as sharing Maria’s story — how her mother lost her job because of time spent caring for her fragile daughter, how the family sank more deeply into poverty and how services needed to be more focused on families. As changes to the CCS system were being discussed, I imagined how they would benefit or hinder Maria’s care and her future.

Read More


Hero Image
gettyimages 138307824
Getty Images
All News button
1
Paragraphs

Objective

To identify the prevalence and predictors of malnutrition among 2-year old children in the Western Highlands of Guatemala.

Methods

Prospective cohort of 852 Guatemalan children in San Lucas Toliman, Guatemala followed from birth to age 2 from May 2008 to December 2013. Socio-demographic, anthropometric, and health data of children was collected at 2 month intervals.

Results

Among the 402 males and 450 females in the cohort, mean weight-for-age Z-score (WAZ) declined from -0.67 ± 1.01 at 1 year to -1.07 ± 0.87 at 2 years, while mean height-for-age Z-score (HAZ) declined from -1.88 ± 1.19 at 1 year to -2.37 ± 0.99 at 2 years. Using multiple linear regression modeling, number of children <5 years old, vomiting in the past week, fever in the past week, and WAZ at 1 year were significant predictors of WAZ at 2 years. Significant predictors of HAZ at 2 years included household size, number of children <5 years old, diarrhea in the past week, WAZ at 1 year, and HAZ at 1 year. Vomiting in the past week and WAZ at 1 year were significant predictors of weight-for-height z-score (WHZ) at 2 years.

Conclusions

Number of children <5 years old, symptoms such as vomiting or diarrhea in the previous week, and prior nutritional status were the most significant predictors of malnutrition in this cohort. Future research may focus on the application of models to develop predictive algorithms for mobile device technology, as well as the identification of other predictors of malnutrition that are not well characterized such as the interaction of environmental exposures with protein consumption and epigenetics.

All Publications button
1
Publication Type
Journal Articles
Publication Date
Journal Publisher
PLoS One
Authors
Paul H. Wise
Paragraphs

Objective

To explore existing barriers and challenges to Early Intervention (EI) referral, enrollment, and service provision for very low birth weight (VLBW; <1500 g) infants.

Methods

We conducted 10 focus groups with parents of VLBW children (n = 44) and 32 interviews with key informants from EI (n = 7), neonatal intensive care units (n = 17), and outpatient clinics (n = 8) at 6 sites in 2 states. We used grounded theory to identify themes about gaps in services.

Results

Both parents and providers found EI helpful. However, they also identified gaps in the current EI system at the levels of eligibility, referral, family receptivity, and service provision and coordination with medical care. Inadequate funding and variable procedures for evaluation may affect children's eligibility. Referrals can be missed as a result of simple oversight or communication failure among hospitals, EI, and families; referral outcomes often are not formally tracked. Families may not be receptive to services as a result of wariness of home visits, social stressors, denial about potential developmental delays, or lack of understanding of the benefits of EI. Once a child is deemed eligible, services may be delayed or terminated early, and EI providers may have little specialized training. Communication and coordination with the child's medical care team is often limited.

Conclusions

Systemic barriers, including funding and staffing issues, state and federal regulations, and communication with families and medical providers, have led to gaps in the EI system. The chronic care model may serve as a framework for integrating community-based interventions like EI with medical care for VLBW children and other vulnerable populations.

All Publications button
1
Publication Type
Journal Articles
Publication Date
Journal Publisher
Academic Pediatrics
Authors
C. Jason Wang
News Type
News
Date
Paragraphs

The health gap between rich and poor children in developing countires is staggeringly high, but Assistant Professor of Medicine Eran Bendavid found that it is shrinking. In his pilot project, "Empirical Evidence on Wealth Inequality and Health in Developing Countries," Bendavid discovered that since the mid-2000s, life expectancies for children under five are starting to converge. How can we continue to close the gap? Watch to find out.

Hero Image
eran wide
All News button
1
Authors
News Type
Q&As
Date
Paragraphs

Robert MacCoun, a professor of law and a senior fellow at the Freeman Spogli Institute for International Studies, relays the potential risks and benefits of legalizing marijuana. His research focuses on drug policy, and he has written extensively about the effects of marijuana from a legal and health perspective.

California, Massachusetts and Nevada all legalized marijuana in the last election. Does this mean the legalization movement has reached a tipping point?  

If Hillary Clinton had won the election, it would probably feel that way, not because she’s a legalization advocate, but because she’d have bigger fish to fry and would probably continue President Obama’s laissez-faire approach. With the Trump administration’s new cabinet, all bets are off. Still, one in five Americans now live in a state where recreational use of marijuana is legal, and that’s a big market. And as the market grows, the industry’s lobbying clout grows.

What are the health risks post-legalization?

That depends on how much consumption levels increase. There are good reasons to expect marijuana prices to fall, which will increase consumption. Because many people use marijuana without health consequences, I worry less about an increase in the number of people using marijuana than about an increase in the number who use it one or more times daily. There is growing evidence that heavy marijuana use is associated with an increased risk of psychosis. We don’t know if it is a true cause-and-effect relationship; let’s hope it is not. But I think the biggest health threat is dependence, which for marijuana is something like getting stuck in the La Brea tar pits — your world just gets smaller and smaller as you get more dysfunctional.

maccoun stanford9 20 14 727 head shot Robert MacCoun, PhD

How can legalizing states combat these risks?

The good news is that legalization makes possible all sorts of regulatory options that weren’t available under prohibition. States should insist that no marijuana products are to be packaged in a way that entices children. Doses should be standardized, and there should be accurate labeling about the THC content. States should discourage products with high levels of THC, and perhaps encourage products with higher levels of cannabidiol (CBD), an ingredient that seems to counteract some of the harmful effects of THC.

The bad news is that the state ballot initiatives didn’t do much more than give lip service to public health and safety, and industry entrepreneurs are pushing back hard against state regulators. I think the industry is being foolish here — they’ve won eight states but still have 42 states to go. I don’t think they realize how quickly a backlash could emerge if those eight states show rising rates of various adverse outcomes.

Could there be any positive health effects of marijuana use?

Absolutely. There are plenty of lines of evidence suggesting medical benefits for some patients. Intriguingly, several new studies suggest that medical marijuana states may be experiencing reduced levels of opioid use and opioid overdoses. The Catch 22 is that the DEA decided not to reschedule marijuana because there isn’t enough rigorous evidence, but there isn’t enough rigorous evidence because the Feds have made such studies almost impossible to conduct.

Some of the biggest health benefits of marijuana will occur if it turns out that marijuana use is a substitute for binge drinking. There are both physiological and economic reasons to think that might be the case, but while some studies show substitution, others show complementarity. For a researcher, one big benefit of legalization is that it is going to help us finally answer a lot of these research questions.

Hero Image
gettyimages 455527832
Bruce Bennett / Getty Images
All News button
1
Paragraphs

The ongoing decline in under-5 mortality ranks among the most significant public and population health successes of the past 30 years. Deaths of children under the age of 5 years have fallen from nearly 13 million per year in 1990 to less than 6 million per year in 2015, even as the world's under-5 population grew by nearly 100 million children. However, the amount of variability underlying this broad global progress is substantial. On a regional level, east Asia and the Pacific have surpassed the Millennium Development Goal target of a two-thirds reduction in under-5 mortality rate between 1990 and 2015, whereas sub-Saharan Africa has had only a 24% decline over the same period. Large differences in progress are also evident within sub-Saharan Africa, where mortality rates have declined by more than 70% from 1990 to 2015 in some countries and increased in others; in 2015, the mortality rate in some countries was more than three times that in others.

What explains this remarkable variation in progress against under-5 mortality? Answering this question requires understanding of where the main sources of variation in mortality lie. One view that is implicit in the way that mortality rates are tracked and targeted is that national policies and conditions drive first-order changes in under-5 mortality. This country-level focus is justified by research that emphasises the role of institutional factors in explaining variation in mortality—factors such as universal health coverage, women's education, and the effectiveness of national health systems. It is argued that these factors, which vary measurably at the country level, fundamentally shape the ability of individuals and communities to affect more proximate causes of child death such as malaria and diarrhoeal disease.

An alternate view has focused on exploring the importance of subnational variation in the distribution of disease. In the USA, studies on the geographical distribution of health care and mortality have been influential for targeting of resources and policy design. Similar studies in developing regions have shown the substantial variability in the distribution and changes of important health outcomes such HIV, malaria, and schistosomiasis—information that can then be used to improve the targeting of interventions. Nevertheless, the relative contribution of within-country and between-country differences in explaining under-5 mortality remains unknown. Improved understanding of the relative contribution of national and sub-national factors could provide insight into the drivers of mortality levels and declines in mortality, as well as improve the targeting of interventions to the areas where they are most needed.

All Publications button
1
Publication Type
Journal Articles
Publication Date
Journal Publisher
The Lancet Global Health
Authors
Eran Bendavid
Subscribe to Children&#039;s health
